Medical notice. This page is for information only. It is not medical advice and does not replace a doctor. Severe abdominal pain needs urgent care — call 112 or go to hospital. See the medical disclaimer.
K86.1 is the ICD-10-CM code for other chronic pancreatitis. Alcohol-induced chronic disease uses K86.0 instead. This page is a US ICD-10-CM FY 2026 coding reference from icd10data.com — not clinical advice. Clinical overview: Chronic pancreatitis. Hub: Pancreatitis ICD-10.
Watch: Osmosis / Elsevier — chronic pancreatitis (medical education). Not medical advice.
https://www.youtube.com/watch?v=WNZGZOWdnXY
K86.1 versus K86.0
Code
Title
When it is used (per Tabular / Applicable To)
K86.0
Alcohol-induced chronic pancreatitis
Chronic pancreatitis attributed to alcohol in the record
K86.1
Other chronic pancreatitis
Chronic pancreatitis that is not coded as alcohol-induced under K86.0
Do not choose K86.0 vs K86.1 from a website guess — follow documentation and the official index. (icd10data — K86.1; K86)
K86.1 — Applicable To
Per ICD-10-CM listings for K86.1, Applicable To includes:
Chronic pancreatitis NOS
Infectious chronic pancreatitis
Recurrent chronic pancreatitis
Relapsing chronic pancreatitis
(“NOS” means not otherwise specified.)
Code Also: K86.81 (EPI)
Code AlsoK86.81 — Exocrine pancreatic insufficiency — when EPI is documented with chronic pancreatitis. EPI is a related K86 code; a dedicated EPI page is planned on this site. List it when the record supports it; do not invent the diagnosis from this article.
Related K86 codes
Description
Note
K86.2
Cyst of pancreas
Related; page planned
K86.3
Pseudocyst of pancreas
Related; page planned
K86.81
Exocrine pancreatic insufficiency
Code Also with K86.1 when applicable
K86.89
Other specified diseases of pancreas
K86.9
Disease of pancreas, unspecified
Acute-on-chronic dual coding
If the same patient has an acute attack and underlying chronic pancreatitis, and separate Alphabetic Index entries exist, ICD-10-CM FY2026 §I.B.8 says: code both, and sequence the acute code (K85.xx) first, then the chronic code (K86.0 or K86.1). Full acute table: Acute pancreatitis ICD-10. Overview: Pancreatitis ICD-10.
Clinical context only (not codes)
NHS: chronic pancreatitis is long-term, currently has no cure, can affect how long you live, and most people live with it for many years. Stop alcohol and smoking to help slow damage. Those statements are clinical context — they do not create ICD codes. Outlook figures: Pancreatitis life expectancy. (NHS, last reviewed 20 October 2025)
Key takeaways
K86.1 = other chronic pancreatitis; K86.0 = alcohol-induced chronic pancreatitis.
Applicable To for K86.1 includes NOS, infectious, recurrent and relapsing chronic pancreatitis.
Code Also K86.81 when EPI is documented.
Acute + chronic → both codes, acute first (§I.B.8).
US ICD-10-CM; verify against the current Tabular List.
FAQ
What is the ICD-10 code for chronic pancreatitis?
Usually K86.1 (other chronic pancreatitis) or K86.0 (alcohol-induced), depending on documentation. (icd10data K86.1)
What is the difference between K86.0 and K86.1?
K86.0 is alcohol-induced chronic pancreatitis. K86.1 is other chronic pancreatitis (including NOS, infectious, recurrent, relapsing per Applicable To).
Do I always add K86.81?
Only when exocrine pancreatic insufficiency is documented — then Code Also K86.81.
How is acute-on-chronic coded?
K85.xx first, then K86.0 or K86.1, when both conditions are coded under §I.B.8. See Acute pancreatitis ICD-10.
Is this the same in every country?
This page describes US ICD-10-CM. National modifications elsewhere may differ.
Medical notice. This page is for information only. It is not medical advice and does not replace a doctor. Severe abdominal pain needs urgent care — call 112 or go to hospital. See the medical disclaimer.
K85 is the ICD-10-CM parent for acute pancreatitis. The parent alone is not billable — you need a code that specifies etiology and the necrosis/infection axis. This is a US ICD-10-CM FY 2026 coding reference from icd10data.com, not clinical advice. Hub: Pancreatitis ICD-10.
Watch: Osmosis / Elsevier — acute pancreatitis (medical education). Not medical advice.
https://www.youtube.com/watch?v=XpAO_0-dTAQ
Why K85 alone is not enough
K85 includes acute pancreatitis (recurrent) and subacute pancreatitis as a category. Claims and clinical documentation need the fifth and sixth characters:
Do not invent etiology or infection status from a website. Coders follow the record and the official Tabular List.
Acute-on-chronic
If documentation supports both acute pancreatitis and chronic pancreatitis with separate Alphabetic Index entries, ICD-10-CM FY2026 §I.B.8 directs coding both and sequencing the acute code first. Pair the appropriate K85.xx with K86.0 or K86.1 as documented. Confirm with your facility coder. Hub overview: Pancreatitis ICD-10.
Key takeaways
Use a specific K85.xx code — not bare K85.
Two axes: etiology and necrosis/infection.
Infected vs uninfected necrosis changes the sixth character (.x2 vs .x1).
Dual-code acute before chronic when both apply (§I.B.8).
This is US ICD-10-CM; other countries may differ.
FAQ
What is the ICD-10 code for acute pancreatitis?
A specific K85.xx code — for example K85.10 for biliary acute pancreatitis without necrosis or infection. The parent K85 is not billable. (icd10data K85)
What code is used for necrotizing acute pancreatitis?
Codes ending in 1 (uninfected necrosis) or 2 (infected necrosis) under the correct etiology branch — e.g. K85.11, K85.12, K85.91, K85.92. Clinical detail: Necrotizing pancreatitis.
Is biliary the same as gallstone pancreatitis for coding?
Biliary acute pancreatitis is the K85.1x branch in ICD-10-CM. Always follow the documented etiology and the Tabular List.
Medical notice. This page is for information only. It is not medical advice and does not replace a doctor. Severe abdominal pain needs urgent care — call 112 or go to hospital. See the medical disclaimer.
This hub lists ICD-10-CM codes for pancreatitis used in the United States (FY 2026, effective 1 October 2025), drawn from icd10data.com. It is a coding reference for clinicians, coders and patients looking up codes — not a diagnosis or billing instruction for your case. Other countries may use different ICD-10 adaptations.
Watch: Alila Medical Media — educational animation of the pancreas. Not medical advice.
Gallstone (biliary) acute disease is coded under K85.1x, not a separate “gallstone pancreatitis” parent in this list. Dedicated gallstone-pancreatitis ICD and pancreatic-cyst ICD pages are planned on this site; codes appear above without inventing live internal links.
Dual coding: acute and chronic together
ICD-10-CM Official Guidelines for Coding and Reporting (FY 2026) §I.B.8: if the same condition is described as both acute and chronic, and separate subentries exist in the Alphabetic Index at the same indentation level, code both and sequence the acute code first. (ICD-10-CM guidelines context via icd10data code pages)
Example pattern (illustrative only): an acute flare coded with a K85.xx code, plus K86.0 or K86.1 for underlying chronic disease when both are documented — acute first. Your facility’s coding policy and the full FY2026 guideline text govern actual claims.
What this page is not
Not a substitute for the official ICD-10-CM Tabular List, Alphabetic Index, or payer rules.
Not clinical advice about acute or chronic disease.
Not a statement that every country uses these exact K85/K86 strings — this is US ICD-10-CM.
Key takeaways
Acute pancreatitis → K85 family; parent K85 is not billable — pick etiology + necrosis/infection.
Chronic → K86.0 (alcohol-induced) or K86.1 (other); Code Also K86.81 for EPI when documented.
Acute + chronic with separate index entries → code both, acute first (§I.B.8).
Always verify against the current Tabular List and your local coding guidance.
FAQ
What is the ICD-10 code for pancreatitis?
There is no single code. Acute disease uses K85.xx; chronic uses K86.0 or K86.1 (and related K86 codes). (icd10data K85; K86)
Is K85 billable by itself?
No. K85 is a non-billable parent. You need a more specific code with the 5th/6th character for etiology and necrosis/infection. See Acute pancreatitis ICD-10.
What is the ICD-10 for chronic pancreatitis?
K86.1 (other chronic pancreatitis) or K86.0 (alcohol-induced chronic pancreatitis), depending on documentation. See Chronic pancreatitis ICD-10.
How do you code acute-on-chronic pancreatitis?
When separate index entries exist for acute and chronic, code both and sequence the acute code first (FY2026 §I.B.8). Confirm with your coder and the official guidelines.
Do these codes apply outside the United States?
This page describes US ICD-10-CM. Other countries may use ICD-10 WHO or national modifications with different detail.
Medical notice. This page is for information only. It is not medical advice and does not replace a doctor. Severe abdominal pain needs urgent care — call 112 or go to hospital. See the medical disclaimer.
Yes. Acute pancreatitis can be life-threatening, but most people recover. About 4 out of 5 improve quickly; about 1 in 5 are severe and can lead to multi-organ failure. Published mortality figures below are group statistics — not a personal prognosis. Know the NHS warning signs and get help early.
Watch: Osmosis / Elsevier — acute pancreatitis (medical education). Not medical advice.
https://www.youtube.com/watch?v=XpAO_0-dTAQ
Direct answer
NHS: acute pancreatitis can be life-threatening. Most people start to get better within a week and leave hospital in 5 to 10 days. Most recover fully. Complications can include necrotizing pancreatitis (pancreatic necrosis), cysts, and later chronic pancreatitis. (NHS, last reviewed 11 March 2026)
NIDDK: either acute or chronic pancreatitis is serious. Complications can include heart, lung or kidney failure and death. Most people with acute pancreatitis get better. (NIDDK)
For how long people live after an attack versus with long-term scarring, see Pancreatitis life expectancy. Severity grades (mild, moderately severe, severe) are explained on 4 stages of acute pancreatitis — clinicians do not use a four-stage Atlanta ladder.
When to call emergency services
NHS says to call 999 or go to A&E if you have sudden severe tummy (abdominal) pain, and especially if:
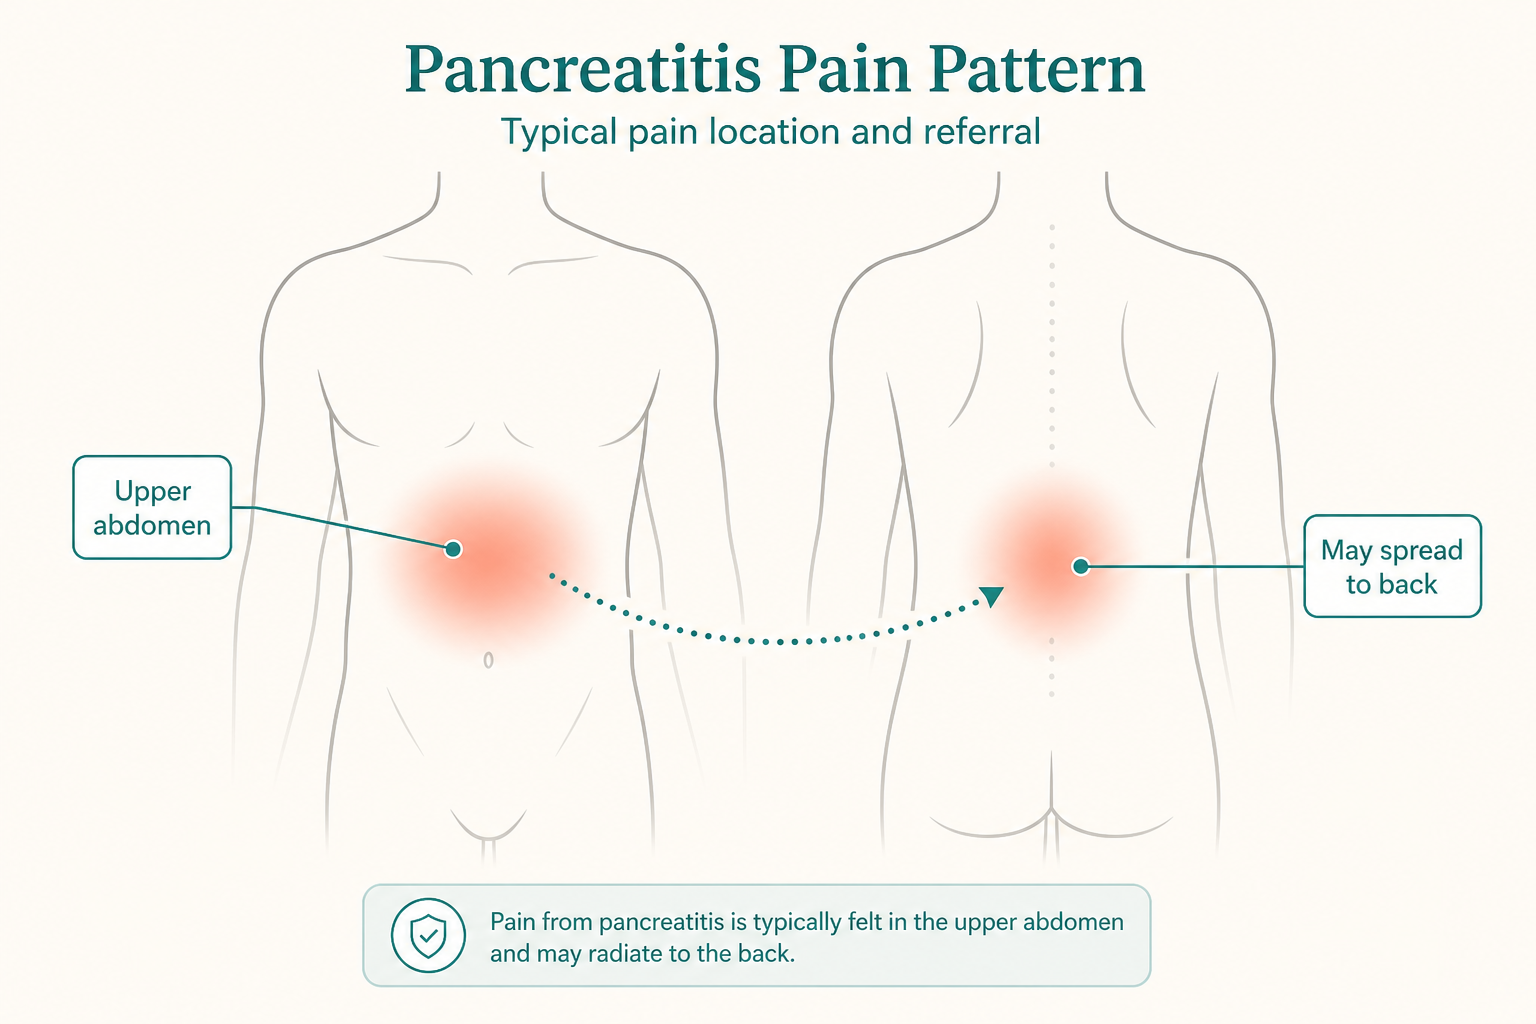
the pain spreads to your back
you also have a swollen or bloated tummy
you have a fast heartbeat or difficulty breathing
you have blue or bruised skin around the belly button, waist or thighs
NHS also says to contact a GP or call 111 as soon as possible if you have sudden severe tummy pain and a high temperature (fever) or feel shivery. In much of Europe the emergency number is 112. Do not wait to “match” yourself to a website table. (NHS, last reviewed 11 March 2026)
How often is pancreatitis fatal?
These are published group figures. They are not your personal risk.
Source
What it reports
Notes
NHS Inform
About 4/5 improve quickly; about 1/5 severe — can cause multi-organ failure and high risk of being fatal
Last updated 24 Aug 2026
NICE NG104 (UK context)
Overall mortality about 5%; in the more severe group (about 25% of cases in that summary) mortality about 25%
Context chapter, not a personal calculator
IAP/APA 2013
Mortality up to 30% in severe acute pancreatitis
Besselink MG, van Santvoort HC, Werner J; Banks PA, Vege SS on executive committee
Banks et al., Gut 2013
Persistent organ failure in the first few days — published mortality as great as 36–50%
Revised Atlanta classification
Werge et al., Pancreatology 2016
Sterile necrosis 13%; infected necrosis 28%; infection + organ failure 35.2%; infected necrosis without organ failure 1.4%
Pooled research; not a personal forecast
NHS Inform (infected necrosis)
Infected pancreatic necrosis in about 1/3 of severe cases; untreated described as almost always fatal; even with care about 1/5 die from organ failure with infected necrosis; SIRS in about 1/10 of severe cases
We do not average these percentages into one “death rate”. Different sources count different groups (all admissions vs severe disease vs necrosis with or without organ failure).
Severe disease, necrosis and organ failure
About 1 in 5 acute cases are severe and can lead to life-threatening complications such as multiple organ failure. (NHS Inform, last updated 24 August 2026)
Necrotizing pancreatitis means some pancreatic or nearby tissue has died. It may stay sterile or become infected. NHS Inform: infected necrosis occurs in around 1 in 3 severe cases, often 2 to 6 weeks after symptoms start. Untreated, they describe it as almost always fatal; even with high standards of care, about 1 in 5 die from organ failure with infected necrosis. Systemic inflammatory response syndrome (SIRS) is described in about 1 in 10 severe cases. (NHS Inform)
Werge M, Novovic S, Schmidt PN and Gluud LL pooled 71 studies (6,970 patients): mortality 13% with sterile necrosis, 28% with infected necrosis, 35.2% when infection and organ failure occurred together, and 1.4% if infected necrosis had no organ failure. (Werge et al., Pancreatology, 2016)
Banks PA, Bollen TL, Dervenis C, Vege SS and colleagues: people who develop persistent organ failure in the first few days are at increased risk of death, with published mortality as great as 36–50% in that group. Infected necrosis on top of persistent organ failure is described as carrying an extremely high mortality. (Banks et al., Gut, 2013)
IAP/APA (Besselink MG, van Santvoort HC, Werner J; Banks PA and Vege SS on the executive committee) note mortality up to 30% in severe acute pancreatitis. (IAP/APA, 2013)
Chronic pancreatitis and death
NHS: chronic pancreatitis is a long-term condition with currently no cure. It can affect how long you live, although this is different for everybody. Most people live with it for many years. Not drinking alcohol and not smoking can help slow damage and reduce other problems. (NHS, last reviewed 20 October 2025)
There is no reliable sourced figure on this site for “dying in your sleep” from pancreatitis. That phrase is common in search results; we do not invent a percentage. If you have sudden severe tummy pain, fever with severe pain, difficulty breathing, or the blue/bruised skin signs NHS lists, treat it as an emergency — not as a sleep-related statistic. See Pancreatitis life expectancy for named survival studies.
What we are not claiming
We do not turn NICE’s 5%, IAP/APA’s up to 30%, Banks’ 36–50%, or Werge’s 13% / 28% / 35.2% into “your” percentage.
We do not invent a “die in your sleep” rate.
We omit unverified blog figures. Named papers and pages are listed on Sources.
Classification and prognosis are done in hospital. Sudden severe tummy pain: call 112.
Key takeaways
Most people with acute pancreatitis recover; NHS: often leave hospital in 5–10 days.
About 1 in 5 cases are severe and can cause multi-organ failure; overall published mortality in UK NICE context is about 5%.
Warning signs that need emergency care include sudden severe tummy pain (especially to the back), bloating, fast heartbeat or breathing difficulty, and blue/bruised skin around the belly button, waist or thighs.
Infected necrosis plus organ failure carries the highest published group mortality in the sources above; sterile necrosis and infection without organ failure are reported differently.
Chronic pancreatitis can affect lifespan; most people still live with it for many years. Stop alcohol and smoking as NHS advises.
These are group figures — ask the team looking after you what applies in your case.
FAQ
Can you die from pancreatitis?
Yes. Acute pancreatitis can be life-threatening. Most people still recover. Severe disease with persistent organ failure or infected necrosis has higher published mortality. (NHS; NICE NG104)
What are pancreatitis death symptoms or warning signs?
NHS lists sudden severe tummy pain (especially spreading to the back), bloating, fast heartbeat or difficulty breathing, and blue or bruised skin around the belly button, waist or thighs as reasons for 999/A&E. Fever or feeling shivery with sudden severe pain needs urgent GP/111 contact. In much of Europe use 112. (NHS)
What is the death rate of acute pancreatitis?
NICE UK context: overall about 5%; about 25% in the more severe subgroup they describe. IAP/APA: up to 30% in severe disease. Banks et al.: as great as 36–50% with persistent organ failure in the first days. These are not interchangeable personal risks. (NICE NG104; IAP/APA, 2013; Banks et al., 2013)
Is necrotizing pancreatitis always fatal?
No. Werge et al. reported much lower mortality when organ failure is absent, and higher mortality when infection and organ failure occur together. See Necrotizing pancreatitis. (Werge et al., 2016)
Can you die from chronic pancreatitis in your sleep?
There is no reliable sourced figure for that specific phrase on this site. Chronic pancreatitis can affect how long you live; NHS says most people live with it for many years. Seek emergency care for the acute warning signs above. (NHS)
Medical notice. This page is for information only. It is not medical advice and does not replace a doctor. Severe abdominal pain needs urgent care — call 112 or go to hospital. See the medical disclaimer.
Most people recover from acute pancreatitis. A minority have severe or necrotizing pancreatitis that can be fatal. Chronic pancreatitis is not cured; alcohol and smoking make the outlook worse. Published survival figures vary by country, cause and era — they are not a personal life expectancy.
Watch: Osmosis / Elsevier — chronic pancreatitis (medical education). Not medical advice.
https://www.youtube.com/watch?v=WNZGZOWdnXY
How to read any number on this page
“Life expectancy” in search results often mixes three different questions: the chance of dying during one hospital admission; how long people with chronic disease live after diagnosis; and modelled population death rates. Those are not interchangeable. Definitions, hospital coding, and treatment eras differ. Unverified percentages are omitted. See also Statistics. Named papers are listed on Sources.
Löhr JM, Dominguez-Munoz E, Rosendahl J, et al., writing the HaPanEU guidelines for United European Gastroenterology, used a median survival of about 20 years after chronic pancreatitis to estimate prevalence. That is a planning figure, not a promise that any one person has twenty years. (Löhr et al., United European Gastroenterology Journal, 2017; PubMed 28344786)
Acute pancreatitis — most people get better
NIDDK: most people with acute pancreatitis get better, and the illness goes away in several days with treatment. Some have a severe form that needs a long hospital stay. The condition can be life-threatening. (NIDDK)
NHS: most people start to get better within a week and can leave hospital in 5 to 10 days. Most recover fully. Acute pancreatitis can still be life-threatening; people are monitored in hospital for complications. (NHS, last reviewed 11 March 2026)
NHS Inform: about 4 out of 5 cases improve quickly and do not cause serious further problems; about 1 in 5 are severe and can lead to life-threatening complications such as multiple organ failure. (NHS Inform, last updated 24 August 2026)
NICE (UK guideline context) states that the overall mortality rate in acute pancreatitis is approximately 5%. In the more severe group — about 25% of cases in that summary — people often need critical care, and the mortality rate is 25%. Those are UK context figures, not a personal risk. (NICE NG104)
The IAP/APA guidelines, coordinated by Besselink MG, van Santvoort HC and Werner J, with Banks PA and Vege SS (Mayo Clinic) on the executive committee, note mortality up to 30% in severe acute pancreatitis. (Working Group IAP/APA, Pancreatology, 2013)
Banks PA, Bollen TL, Dervenis C, Vege SS and colleagues wrote that people who develop persistent organ failure in the first few days are at increased risk of death, with published mortality as great as 36–50% in that group. Infected necrosis on top of persistent organ failure is described as carrying an extremely high mortality. Mild Atlanta disease, by contrast, usually resolves in the first week. (Banks et al., Gut, 2013; PubMed 23100216)
Severe and necrotizing disease
Necrotising (necrotizing) pancreatitis is a type of acute disease — some pancreatic or nearby tissue has died — not a separate illness. It may stay sterile or become infected. Details: Necrotizing pancreatitis.
Werge M, Novovic S, Schmidt PN and Gluud LL pooled 71 studies (6,970 patients). Mortality was 13% with sterile necrosis and 28% with infected necrosis; 35.2% when infection and organ failure occurred together; 1.4% if infected necrosis had no organ failure. NHS Inform estimates around 1 in 5 for death from organ failure in infected pancreatic necrosis even with high standards of care; untreated, they describe it as almost always fatal. We do not average those numbers. (Werge et al., Pancreatology, 2016; PubMed 27449605; NHS Inform)
Chronic pancreatitis — no cure, many years for most
NHS: chronic pancreatitis is a long-term condition. There is currently no cure. The condition can affect how long you live, although this is different for everybody. Most people live with it for many years. Damage usually gets worse over time and cannot be reversed — but not drinking alcohol and not smoking can help slow it and reduce other problems. (NHS, last reviewed 20 October 2025)
NHS Inform: people who do not smoke and avoid drinking alcohol tend to experience less pain and live longer than those who continue to drink and smoke after a diagnosis. If you continue to drink, they say you are more likely to die from a complication of chronic pancreatitis. (NHS Inform — Chronic pancreatitis, last updated 18 March 2026)
NIDDK: when people with chronic pancreatitis caused by alcohol continue to drink, the condition is more likely to lead to severe complications and even death. Smoking with pancreatitis may raise pancreatic cancer risk. (NIDDK — Treatment)
Lowenfels AB, Maisonneuve P, Cavallini G, Ammann RW, Lankisch PG, Andersen JR, DiMagno EP (Mayo Clinic) and colleagues followed 2,015 people with chronic pancreatitis at seven centres in six countries. Overall survival was 70% at 10 years (95% CI 68–73%) and 45% at 20 years (95% CI 41–49%) — significantly less than the background population. There were 559 deaths versus 157.4 expected (standardised mortality ratio 3.6; 95% CI 3.3–3.9). Smoking, continued drinking, older age at diagnosis, and cirrhosis increased the risk of death in that cohort. Those figures are from 1994; care and smoking rates have changed. They are not a personal forecast. (Lowenfels et al., Am J Gastroenterol, 1994; Mayo Clinic research record)
HaPanEU’s median survival of about 20 years is consistent with using a long course to estimate prevalence (around 120 per 100,000 if incidence is 5–10 per 100,000). It is not an NHS “you have 20 years” statement. (Löhr et al., 2017)
NHS Inform estimates that for every 100 people with chronic pancreatitis, only 1 or 2 will develop pancreatic cancer — a higher risk than the general population, still a minority of patients. NHS also lists a higher pancreatic cancer risk. That is not the same as a life-expectancy number. (NHS Inform; NHS)
Comparison table
Acute pancreatitis
Chronic pancreatitis
Usual course
Most recover; NHS: often 5–10 days in hospital
No cure; NHS: most people live with it for many years
Published death risk in one spell
NICE: overall about 5%; about 25% in the severe subgroup they describe
Not a single-admission figure — a long-term condition
Severe / necrosis
IAP/APA: mortality up to 30% in severe disease; Banks et al.: up to 36–50% with persistent organ failure
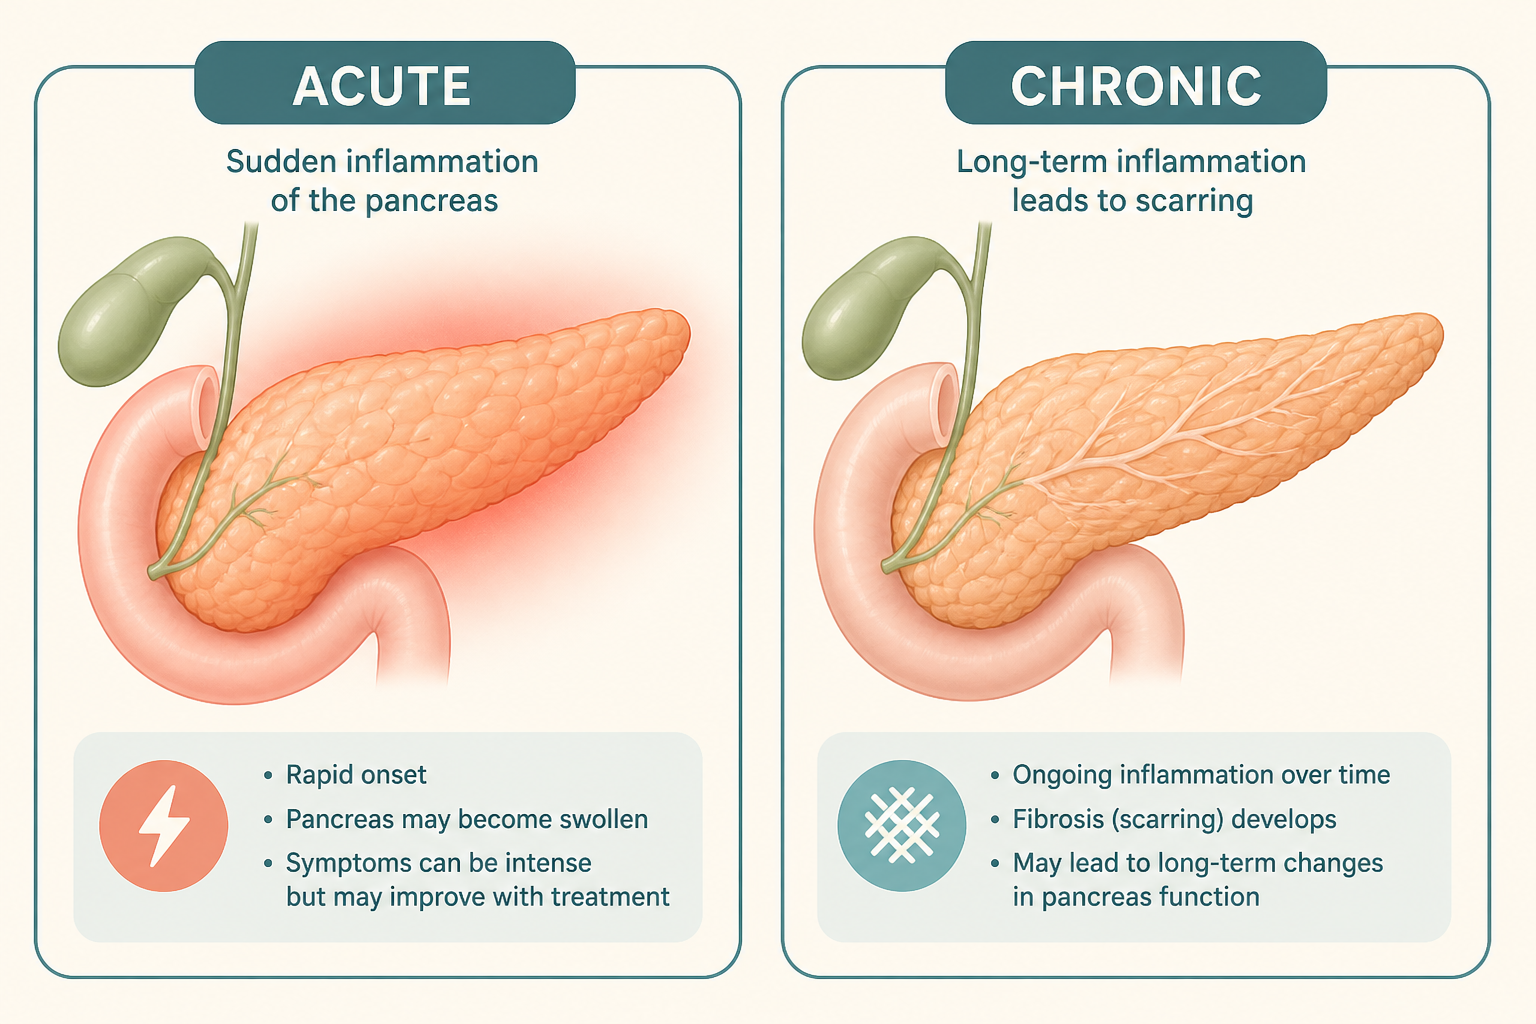
Repeated acute attacks can scar the gland permanently
What worsens outlook
Persistent organ failure; infected necrosis; continuing to drink or smoke
Continuing alcohol (especially if alcohol was the cause); smoking; cirrhosis in older series
What clinicians emphasise
Hospital care, treat the cause, prevent the next attack
Stop alcohol, stop smoking, enzymes, pain and diabetes care
We do not turn NICE’s 5% or Werge’s 28% into “your” percentage.
We do not give a European “average life expectancy in years” for pancreatitis. HaPanEU’s 20-year median and Lowenfels’ 10- and 20-year survival come from different methods and decades.
We omit unverified blog figures and any number we could not trace to NHS, NICE, NIDDK, Mayo Clinic, HaPanEU, Atlanta, IAP/APA, or a named paper above.
Population modelled deaths (GBD) on the statistics page are not individual life expectancy.
Ask the team looking after you what applies in your case.
FAQ
Does pancreatitis shorten life expectancy?
A mild acute attack that resolves often does not. Severe acute disease, especially with persistent organ failure or infected necrosis, can be fatal. Chronic pancreatitis can affect how long you live; NHS says most people still live with it for many years. (NHS; NICE NG104)
What is the survival rate of acute pancreatitis?
NICE’s UK context figure is about 5% overall mortality, and about 25% in severe cases as they define them. IAP/APA cite mortality up to 30% in severe disease. Most people still recover. (NICE NG104; IAP/APA, 2013; NHS)
How long do people live with chronic pancreatitis?
There is no single number. HaPanEU used a median survival of about 20 years to estimate prevalence. Lowenfels et al. reported 70% survival at 10 years and 45% at 20 years in a 1994 multicentre cohort. NHS: most people live with it for many years. (Löhr et al., 2017; Lowenfels et al., 1994; NHS)
Does stopping alcohol and smoking change the outlook?
Yes, according to NHS, NHS Inform and NIDDK. Continuing to drink after alcohol-related chronic disease makes severe complications and death more likely. People who stop smoking and alcohol tend to have less pain and live longer in NHS Inform’s wording. (NHS; NHS Inform; NIDDK)
Is necrotizing pancreatitis always fatal?
No. Pooled research has reported much lower mortality when organ failure is absent, and higher mortality when infection and organ failure occur together. See Necrotizing pancreatitis. (Werge et al., 2016)
Can I calculate my own life expectancy from this table?
No. Classification and prognosis are done in hospital. Sudden severe tummy pain is a reason to call 112. (NHS)
Last editorial check: 29 August 2026. Not medically reviewed by a clinician.
Emergency warning signs (NHS 999/A&E criteria) and a side-by-side table of published death-risk figures are on Can you die from pancreatitis? That page does not invent a “die in your sleep” statistic.
Medical notice. This page is for information only. It is not medical advice and does not replace a doctor. Severe abdominal pain needs urgent care — call 112 or go to hospital. See the medical disclaimer.
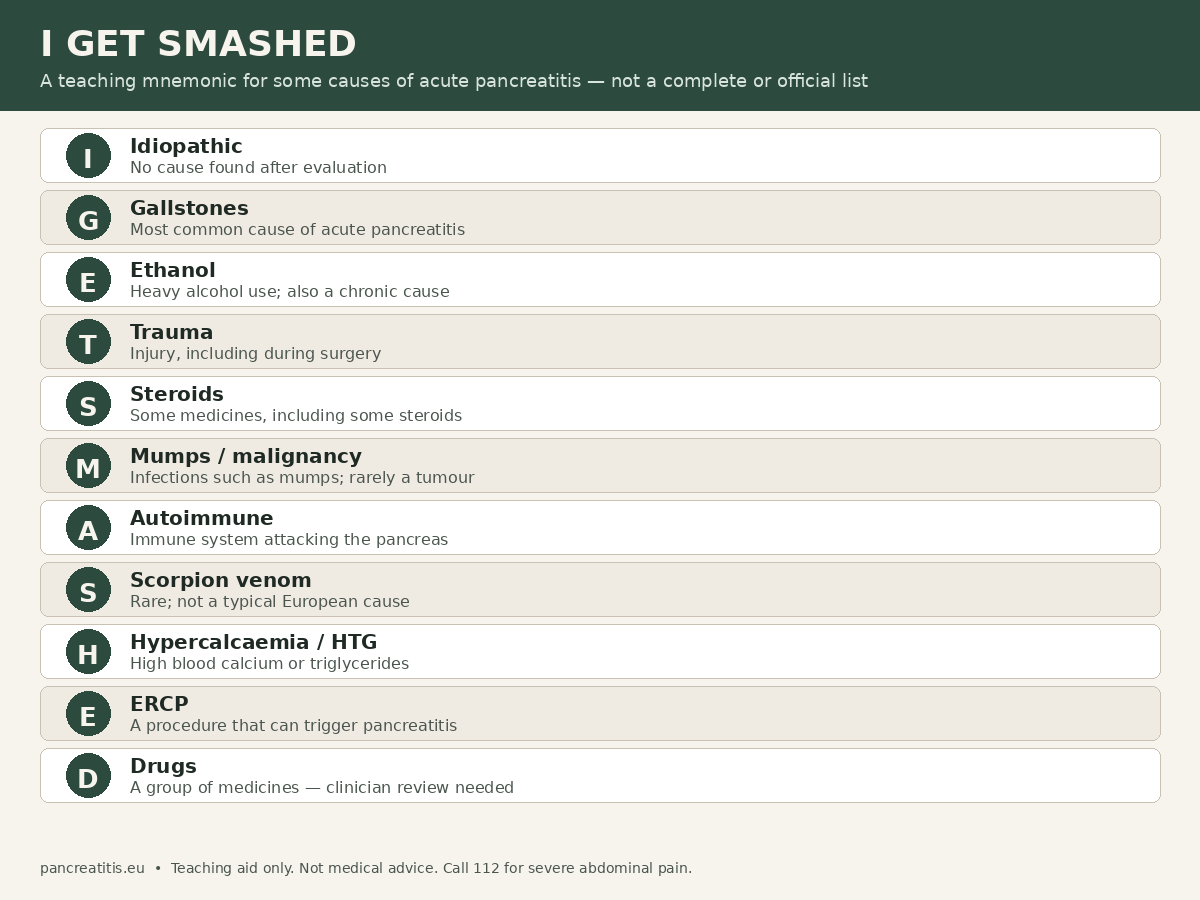
I GET SMASHED is a teaching mnemonic for causes of acute pancreatitis, not an official or complete list. Gallstones and alcohol (ethanol) cause most attacks. The other letters are less common reminders for students. It does not replace a hospital work-up. Sudden severe tummy pain needs 112, not a mnemonic.
Watch: Osmosis / Elsevier — acute pancreatitis (medical education). Not medical advice.
https://www.youtube.com/watch?v=XpAO_0-dTAQ
What the mnemonic is — and is not
Medical students use I GET SMASHED to remember possible causes of acute pancreatitis. It is a memory aid, not a guideline and not a ranking of how often each cause occurs. Banks PA, Bollen TL, Dervenis C, Vege SS (Mayo Clinic) and colleagues, in the revised Atlanta classification, described how clinicians diagnose acute pancreatitis (two of three: typical pain; lipase or amylase at least three times the upper limit of normal; characteristic imaging). Atlanta does not use this mnemonic. (Banks et al., Gut, 2013; PubMed 23100216)
NHS, NIDDK and Mayo Clinic Staff all put gallstones and heavy alcohol use first. Everything else on the list is less common. Some real causes — smoking, inherited conditions such as cystic fibrosis, pancreas divisum — do not get their own letter. For the patient-facing list, see Symptoms and causes and What is pancreatitis. (NHS, last reviewed 11 March 2026; NIDDK; Mayo Clinic, dated 31 October 2025)
The IAP/APA guidelines, coordinated by Besselink MG, van Santvoort HC and Werner J, with Banks PA and Vege SS on the executive committee, ask clinicians to look for cause on admission: history (alcohol, medicines, known gallstones, recent ERCP), examination, blood tests (liver enzymes, calcium, triglycerides), and right-upper-quadrant ultrasound. That is a work-up, not a mnemonic recitation. (Working Group IAP/APA, Pancreatology, 2013)
Letter by letter
Letter
Stands for
Plain meaning
How common, in sourced pages
I
Idiopathic
No cause found after tests
Mayo Clinic Staff and NIDDK: sometimes a cause is never found. ACG: unknown in nearly a third of chronic cases after extensive evaluation — that figure is for chronic disease, not a rate for every acute attack.
G
Gallstones
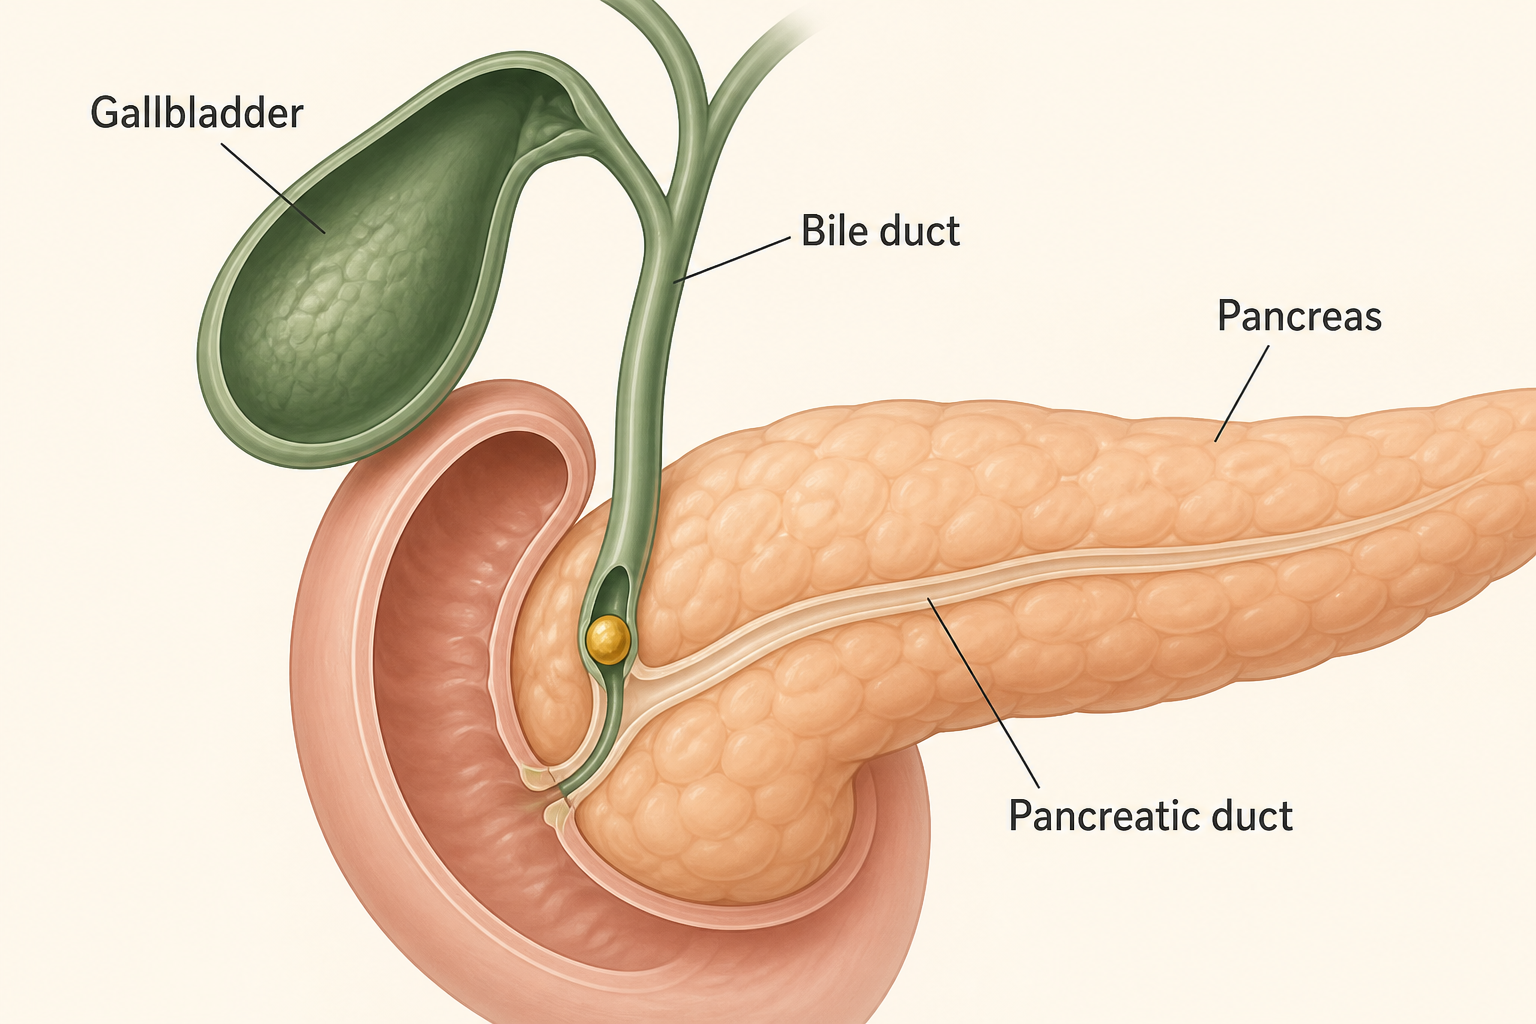
Stones can block the opening of the pancreas (gallstone pancreatitis)
NHS and NIDDK: the most common cause of acute disease. NHS Inform: around half of cases. NICE: around 50%.
E
Ethanol
Heavy alcohol use
NHS: the other leading cause. NHS Inform: about a quarter. NICE: around 25%. Dominant in much of eastern Europe (Roberts et al.).
T
Trauma
Injury to the pancreas, including during surgery
NHS and Mayo Clinic Staff list injury, including surgery and endoscopy. Uncommon compared with stones and alcohol.
S
Steroids
Certain steroid medicines
NHS lists certain steroids among medicines that can trigger pancreatitis. Not every steroid course. Do not stop a prescribed medicine from this page.
M
Mumps / malignancy
Viral infection such as mumps; rarely a cancer blocking a duct
NHS lists mumps and pancreatic cancer among less common causes. NHS Inform also mentions measles. Cancer is a different disease that can occasionally trigger pancreatitis.
A
Autoimmune
The immune system attacking the pancreas
Mayo Clinic Staff list an autoimmune condition among causes of chronic disease. NHS lists lupus among less common acute causes, and the immune system attacking the gland among chronic causes.
S
Scorpion
Sting of certain scorpions
A rare teaching example, not a European cause. Bartholomew C. described acute pancreatitis after stings of Tityus trinitatis in Trinidad (1970).
H
Hypercalcaemia / hypertriglyceridaemia
High blood calcium; high blood fats (triglycerides)
NHS lists hypercalcaemia. Mayo Clinic Staff, NIDDK and ACG list high triglycerides and high calcium. This page does not invent a laboratory cut-off.
E
ERCP
Endoscopic retrograde cholangiopancreatography
NIDDK lists ERCP done for another condition as a cause. Mayo Clinic Staff note that ERCP may trigger acute pancreatitis. IAP/APA include recent ERCP in the admission history.
D
Drugs
Certain other medicines
NHS: some heart and epilepsy medicines. NHS Inform: some antibiotics, weight-loss and chemotherapy medicines. Mayo Clinic Staff: “certain medicines”. Culprit drugs belong to the clinical team, not a website list.
The two letters that actually matter for most people
Gallstones and ethanol are not two equal items on a twelve-item list. They are the usual answers.
NIDDK: the most common cause of acute pancreatitis is gallstones. Stones passing through or lodging in a bile or pancreatic duct inflame the pancreas. NHS: the most common causes are gallstones and drinking a lot of alcohol. NICE (UK) puts the split at around 50% gallstones, 25% alcohol, and 25% other factors. Across Europe, Roberts SE and colleagues found gallstones dominant in much of the south (including Croatia) and alcohol more often dominant in much of the east. (NIDDK; NHS; NICE NG104; Roberts et al.)
If gallstones caused the attack, hospital care may later include ERCP when a bile duct is blocked, and gallbladder removal when it is safe. If alcohol caused it, stopping drinking is the prevention. Continuing to drink after acute pancreatitis can lead to more attacks and to chronic disease. (NIDDK — Treatment; NHS; Mayo Clinic — Diagnosis & treatment)
Letters that confuse people
Scorpion is in the mnemonic because Bartholomew documented pancreatitis after Tityus trinitatis stings in Trinidad. Over two months, 30 people were admitted after stings; acute pancreatitis developed in 24. All recovered in that series. It is a real, geographically limited cause — not something to look for in a European emergency department unless the history actually includes a sting. (Bartholomew, 1970)
Steroids and drugs are real but uncommon. NHS names certain steroids and some heart and epilepsy medicines; NHS Inform adds some antibiotics, weight-loss and chemotherapy medicines. Mayo Clinic Staff advise talking with a clinician about medicines rather than stopping them from a list. ACG’s patient topic (originally Banks PA) includes “drug induced pancreatitis — avoid offending medication” among prevention points, which is a clinical decision. (NHS; NHS Inform; Mayo Clinic; ACG)
ERCP is both a cause of pancreatitis and a treatment used when gallstones are stuck in the bile duct. Mayo Clinic Staff note that ERCP may trigger acute pancreatitis, so it is not for everyone. IAP/APA reserve urgent ERCP for cholangitis or persistent bile-duct obstruction, not as a routine test. (Mayo Clinic; IAP/APA, 2013)
What the mnemonic misses
Smoking does not have a letter. Mayo Clinic Staff note that people who smoke cigarettes are about three times more likely to develop pancreatitis than people who do not, and that quitting can decrease risk. ACG lists smoking among causes of acute disease and among the common causes of chronic disease. (Mayo Clinic; ACG)
Inherited conditions (including the gene that causes cystic fibrosis) and pancreas divisum appear on NIDDK and NHS chronic pages. They are real; they simply do not fit the rhyme. (NIDDK; NHS — Chronic pancreatitis)
Is I GET SMASHED an official list of pancreatitis causes?
No. It is a teaching mnemonic. NHS, NIDDK, Mayo Clinic and IAP/APA do not use it as a classification. Gallstones and alcohol still account for most acute cases. (NHS; NICE NG104)
What does each letter in I GET SMASHED stand for?
Idiopathic, Gallstones, Ethanol, Trauma, Steroids, Mumps/malignancy, Autoimmune, Scorpion, Hypercalcaemia/hypertriglyceridaemia, ERCP, Drugs. See the table above. It is not complete.
Do I need every letter checked after one attack?
No. IAP/APA describe a focused admission work-up. Which tests you need is a hospital decision. (IAP/APA, 2013)
Can scorpion sting cause pancreatitis in Europe?
The classic papers describe Tityus trinitatis in Trinidad. It is a rare teaching example. European cases are not the reason the letter exists. (Bartholomew, 1970)
Should I stop my steroid or epilepsy medicine?
No — not from this page. NHS lists certain medicines as uncommon triggers. Changing a prescription is a clinician’s job. (NHS; Mayo Clinic)
When should I call 112?
Sudden severe tummy pain, especially spreading to the back, with vomiting, fever, a fast heartbeat, or difficulty breathing. A mnemonic is not first aid. (NHS)
Medical notice. This page is for information only. It is not medical advice and does not replace a doctor. Severe abdominal pain needs urgent care — call 112 or go to hospital. See the medical disclaimer.
Necrotizing pancreatitis means inflammation of the pancreas is severe enough that some pancreatic tissue, nearby fat, or both, dies (necrosis). What causes necrotizing pancreatitis is usually the same as other severe acute pancreatitis — most often gallstones or heavy alcohol use. Infected necrosis is more dangerous than sterile necrosis. Survival figures vary widely; they are not a personal prognosis.
Watch: Osmosis / Elsevier — acute pancreatitis (medical education). Not medical advice.
https://www.youtube.com/watch?v=XpAO_0-dTAQ
What “necrosis” means here
The pancreas makes digestive enzymes that are meant to switch on in the intestine. If they switch on too soon, they can injure the gland. When inflammation is intense enough to interrupt blood supply, tissue can die. That dead tissue is necrosis. (NIDDK; Mayo Clinic, dated 31 October 2025)
Banks PA, Bollen TL, Dervenis C, Vege SS (Mayo Clinic) and colleagues described necrotising (necrotizing) pancreatitis in the revised Atlanta classification as one of two morphologic types of acute pancreatitis. The other is interstitial oedematous disease, in which the gland is swollen but tissue is not dead. Necrosis can involve the pancreas itself, the tissues around it, or both. It is a type, not a numbered “stage”. See 4 stages of acute pancreatitis. (Banks et al., Gut, 2013; PubMed 23100216)
NHS lists pancreatic necrosis among complications of acute pancreatitis: some tissue dies, and infection can lead to sepsis. Most people with an acute attack never develop this picture. NHS Inform states that about 4 out of 5 cases improve quickly, while about 1 in 5 are severe. (NHS, last reviewed 11 March 2026; NHS Inform, last updated 24 August 2026)
NHS Inform explains infected pancreatic necrosis in plain language: high inflammation can interrupt the blood supply; dead tissue is then vulnerable to bacteria; untreated, the infection can spread in the blood and cause organ failure. They estimate it occurs in around 1 in 3 severe cases, usually 2 to 6 weeks after symptoms start. (NHS Inform)
What causes necrotizing pancreatitis
There is not a separate “necrotizing cause list”. The usual triggers of acute pancreatitis are the usual triggers here. Whether an attack stays mild or becomes necrotising depends on how severe the inflammation and organ failure become — that is not something a website can predict for one person.
The most common causes of acute pancreatitis are:
Gallstones, which can block the opening of the pancreas
Drinking a lot of alcohol
(NHS; NIDDK; ACG, patient topic originally by Banks PA, later updated)
NHS Inform puts gallstones at around half of cases and alcohol at about a quarter. Across Europe the mix shifts: gallstones dominate in much of southern Europe; alcohol is more often dominant in much of the east. (NHS Inform; Roberts et al., PubMed 28159463)
Less common causes, listed by NHS, NIDDK, Mayo Clinic Staff, and ACG, include injury (including during surgery), certain medicines, high blood triglycerides, high blood calcium (hypercalcaemia), procedures such as ERCP, some infections (NHS mentions mumps), pancreatic cancer (a different disease that can occasionally trigger pancreatitis), and no identified cause (idiopathic). (NHS; NIDDK; Mayo Clinic; ACG)
The IAP/APA guidelines, coordinated by Besselink MG, van Santvoort HC and Werner J, with Banks PA and Vege SS on the executive committee, recommend determining cause on admission using history (alcohol, medicines, known gallstones, recent ERCP), examination, blood tests (liver enzymes, calcium, triglycerides), and right-upper-quadrant ultrasound. (Working Group IAP/APA, Pancreatology, 2013)
NHS Inform notes that little is known about why some people develop severe disease; factors thought to raise that risk include age 70 or over, obesity (BMI 30 or above), drinking two or more alcoholic drinks a day, and smoking. That is not the same as a cause of necrosis itself. (NHS Inform)
Sterile versus infected necrosis
This distinction matters for outlook and treatment.
Sterile necrosis
Infected necrosis
Meaning
Dead tissue without proven infection
Bacteria in the necrotic collection
How it may be suspected
Imaging showing necrosis; the person may still be recovering
Persistent fever, rising inflammatory markers, gas in a collection on CT, or a sample that grows bacteria
Typical course
Many people can be managed without an operation
Often needs antibiotics and, if the person is deteriorating, drainage — usually delayed until the collection is walled-off
Mortality in published series
Lower than infected necrosis, but not zero — especially with organ failure
Higher; still varies widely
IAP/APA state that clinical signs (persistent fever, rising inflammatory markers) and imaging (gas in collections) predict infected necrosis in most patients; routine needle aspiration is not indicated. The vast majority of sterile necrotising pancreatitis can be managed without catheter drainage or necrosectomy. A small proportion of stable patients with documented infection can be managed with antibiotics alone. (IAP/APA, 2013)
Werge M, Novovic S, Schmidt PN and Gluud LL pooled 71 studies (6,970 patients) in Pancreatology (2016). 801 of 2,842 patients with infected necrosis died (28%); 537 of 4,128 with sterile necrosis died (13%). The odds of death were more than twice as high with infection (odds ratio 2.57; 95% CI 2.00–3.31). Mortality was 35.2% with infected necrosis and organ failure, 19.8% with sterile necrosis and organ failure, and 1.4% with infected necrosis without organ failure. Those are pooled research figures, not a forecast for one person, and they mix older and newer treatment eras. (Werge et al., Pancreatology, 2016; PubMed 27449605)
Dellinger EP, Forsmark CE, Layer P, et al. used infected necrosis plus persistent organ failure as the critical category in the determinant-based classification — the sickest group in that system, not an Atlanta “stage 4”. (Dellinger et al., Ann Surg, 2012; PubMed 22735715)
Hospital treatment (overview — not a protocol)
There is no specific medicine that treats pancreatitis itself. Care is supportive and then directed at the cause and at complications. (Mayo Clinic — Diagnosis & treatment; NIDDK)
Typical hospital measures include intravenous fluids, pain relief, and nutrition (by mouth when it is safe, or by feeding tube). IAP/APA recommend against routine intravenous antibiotic prophylaxis to prevent infection. Antibiotics are used when infection is suspected or confirmed. (IAP/APA, 2013; NHS)
If gallstones caused the attack, ERCP may be used when there is cholangitis or a blocked bile duct; gallbladder removal is often planned once it is safe. NIDDK notes that operating to remove the gallbladder within a few days of admission can lower complications in appropriate mild gallstone cases; if pancreatitis is severe, surgery may be delayed while complications are treated. (IAP/APA, 2013; NIDDK)
For infected necrosis, IAP/APA recommend a step-up approach: image-guided percutaneous drainage or endoscopic drainage first, then necrosectomy only if needed. Invasive intervention should be delayed, where possible, until at least 4 weeks, so the collection can become walled-off. The 2025 IAP revision keeps that step-up approach (strong recommendation). These documents are written for clinicians, not for self-treatment. (IAP/APA, 2013; IAP 2025)
Mayo Clinic Staff note that pancreatic infections are serious and may need procedures to remove infected tissue. ACG’s patient topic (originally Banks PA) likewise says surgery may be needed if there is a severe infection called necrosis. (Mayo Clinic; ACG)
This site does not list drug doses, antibiotic names as a protocol, or “what to ask the surgeon to do”. Those decisions belong to the hospital team.
Survival rate — published ranges, not a personal figure
The necrotizing pancreatitis survival rate is better than older textbooks sometimes implied, and it still depends on organ failure, infection, age, other illnesses, and how care is organised. Published numbers vary widely. They should not be read as “your” percentage. For the wider picture of acute versus chronic outlook, see Pancreatitis life expectancy and Statistics.
Verified figures used on this page:
Most acute pancreatitis is not necrotising; about 4 of 5 attacks improve quickly. (NHS Inform)
IAP/APA: mortality up to 30% in severe acute pancreatitis. (IAP/APA, 2013)
Banks et al.: persistent organ failure in the first few days — published mortality as great as 36–50%; infected necrosis plus persistent organ failure described as extremely high mortality. (Banks et al., Gut, 2013)
Werge et al.: pooled 28% mortality in infected necrosis versus 13% in sterile necrosis; 35.2% when infection and organ failure occur together; 1.4% if infected necrosis has no organ failure. (Werge et al., 2016)
NHS Inform: even with high standards of care, the risk of dying from organ failure in infected pancreatic necrosis is estimated at around 1 in 5; untreated, they describe it as almost always fatal. (NHS Inform)
We do not average those numbers. They come from different methods and years.
After hospital, NHS and NIDDK both stress that another attack is possible. Stopping alcohol (even if alcohol was not the cause), stopping smoking, a lower-fat eating pattern, and finishing the plan for gallstones or high triglycerides all reduce that risk. Continuing to drink after acute pancreatitis can lead to more attacks and to chronic pancreatitis. (NHS; NIDDK)
What causes necrotizing pancreatitis?
The same things that cause other severe acute attacks — most often gallstones or heavy alcohol use, plus less common triggers such as high triglycerides, some medicines, ERCP, trauma, or no found cause. Necrosis is how severe inflammation can damage tissue, not a separate cause list. (NHS; NIDDK)
Is necrotizing pancreatitis the same as severe pancreatitis?
Not exactly. Atlanta severity is about persistent organ failure. Necrotising disease is a morphologic type. They often overlap, but a collection of dead tissue and organ failure are classified separately. (Banks et al., Gut, 2013)
What is the survival rate?
It varies widely. Pooled research has reported about 13% mortality with sterile necrosis and 28% with infected necrosis, and much higher figures when organ failure is also present. NHS Inform estimates around 1 in 5 for death from organ failure in infected necrosis even with good care. None of these is a personal forecast. (Werge et al., 2016; NHS Inform)
Do all people with necrosis need surgery?
No. IAP/APA say most sterile necrosis is managed without intervention. When infection needs a procedure, the usual first step is drainage, often delayed until about four weeks, not immediate open surgery. (IAP/APA, 2013)
Are antibiotics given to everyone?
No. Routine prophylactic intravenous antibiotics are not recommended. Antibiotics are used for suspected or proven infection. (IAP/APA, 2013)
When should I call 112?
Sudden severe tummy pain, especially spreading to the back, with vomiting, fever, a fast heartbeat, or difficulty breathing. Do not wait to “see if it is necrosis”. (NHS)
Last editorial check: 29 August 2026. Not medically reviewed by a clinician.
Infected necrosis mortality ranges (Werge et al.; NHS Inform) also appear in the warning-signs article Can you die from pancreatitis? Necrosis/infection status maps to the sixth character of K85.xx — see Acute pancreatitis ICD-10.
Medical notice. This page is for information only. It is not medical advice and does not replace a doctor. Severe abdominal pain needs urgent care — call 112 or go to hospital. See the medical disclaimer.
People search for “4 stages of acute pancreatitis”, but clinicians do not use a four-stage Atlanta scale. The revised Atlanta classification (2012) uses three severity grades — mild, moderately severe, and severe — plus two morphologic types and an early versus late phase. Banks PA, Bollen TL, Dervenis C, et al. described that system in Gut (2013).
Watch: Osmosis / Elsevier — acute pancreatitis (medical education). Not medical advice.
https://www.youtube.com/watch?v=XpAO_0-dTAQ
What people mean by “4 stages”
The phrase is common online. It is not how international consensus classifies the illness. Three ideas get mixed together:
A four-category system — Dellinger EP, Forsmark CE, Layer P, et al. described a determinant-based classification the same year: mild, moderate, severe, and critical. Those are categories of severity, not a sequence every patient walks through. (Dellinger et al., Ann Surg, 2012; PubMed 22735715)
Four types of fluid collection — Atlanta names four local collections. They are imaging findings, not four steps of one disease. (Banks et al., Gut, 2013)
This page puts those systems side by side so the search query is answered without inventing a fake “stage 1–4” Atlanta ladder. For the basic picture, see What is pancreatitis and Acute pancreatitis.
Atlanta criteria: what clinicians actually use
The 2012 revision, published in Gut in 2013, is a classification for adults, not a treatment guideline. It asks four practical questions:
Is it acute pancreatitis? Two of three features must be present.
How severe is it? Mild, moderately severe, or severe.
When in the course is this? Early phase or late phase.
The original 1992 Atlanta meeting used a simpler mild-versus-severe split. The revision added the middle grade and tightened the language for collections and necrosis. (Banks et al., Gut, 2013)
The IAP/APA guidelines, coordinated by Besselink MG, van Santvoort HC and Werner J, with Banks PA and Vege SS (Mayo Clinic) on the executive committee, use the same Atlanta language for diagnosis and severity. (Working Group IAP/APA, Pancreatology, 2013)
Diagnosis (Atlanta “2 of 3”): abdominal pain consistent with the disease; serum lipase or amylase at least three times the upper limit of normal; characteristic findings on imaging. Two of those three make the diagnosis. Imaging is often not needed at the door. When a CT is used to look for necrosis, IAP/APA advise waiting at least 72–96 hours after symptoms start. NHS diagnoses with blood tests and sometimes a CT, and treats in hospital straight away. (Banks et al.; IAP/APA, 2013; NHS, last reviewed 11 March 2026)
Comparison table
What you may hear
What it actually is
Sequential “stages”?
“4 stages of acute pancreatitis”
Informal search phrase; not an Atlanta scale
No official four-step Atlanta ladder
Revised Atlanta severity
Three grades: mild / moderately severe / severe
No — the grade depends on how long organ failure lasts
Mild is the most common form: no organ failure and no local or systemic complications. Banks and colleagues wrote that it usually resolves in the first week. (Banks et al., Gut, 2013)
NHS Inform (NHS 24) states that about 4 out of 5 cases improve quickly without serious further problems, while about 1 in 5 are severe and can lead to life-threatening complications such as multiple organ failure. Most people leave hospital in 5 to 10 days. (NHS Inform, last updated 24 August 2026; NHS)
Moderately severe means transient organ failure (less than 48 hours), and/or local complications, and/or a flare of a pre-existing illness. It can still mean a longer stay. (Banks et al., Gut, 2013)
Severe means persistent organ failure lasting more than 48 hours (one organ or several). Banks and colleagues reported that people who develop persistent organ failure in the first few days are at increased risk of death, with published mortality as great as 36–50% in that group. Infected necrosis on top of persistent organ failure is described as carrying an extremely high mortality. Those figures are not a personal prognosis. (Banks et al., Gut, 2013)
IAP/APA note a reported annual incidence of 13–45 per 100,000, and mortality up to 30% in severe disease. Severity is reassessed; Atlanta suggests review at 24 hours, 48 hours, and 7 days. (IAP/APA, 2013; Banks et al.)
Two types, two phases — not four stages
Interstitial oedematous pancreatitis: the gland is swollen; tissue is inflamed but not dead. Necrotising pancreatitis: some pancreatic tissue, nearby fat, or both, has died. Necrosis may stay sterile or become infected. Necrotising disease is a morphologic type, not “stage 4”. See Necrotizing pancreatitis. (Banks et al., Gut, 2013)
The early phase is usually over by the end of the first week (it can stretch into the second). The question is whether organ failure appears and whether it lasts beyond 48 hours. The late phase is about collections, necrosis that may become infected, and procedures if the person is not recovering. IAP/APA recommend delaying invasive treatment of infected necrosis, where possible, until about 4 weeks. (Banks et al.; IAP/APA, 2013; IAP 2025, DOI 10.1016/j.pan.2025.04.020)
Typical symptoms are sudden upper-abdominal pain (often to the back), nausea, vomiting, fever, and a fast heartbeat. That is an emergency, not a numbered stage. Call 112. (NHS; NIDDK)
Four collections — types, not a ladder
These are the four local collections Atlanta names. They are not a pathway every patient follows.
Collection
Typical setting
Usual timing
Plain meaning
Acute peripancreatic fluid collection (APFC)
Interstitial (oedematous) pancreatitis
First 4 weeks
Fluid around the pancreas without solid necrosis
Acute necrotic collection (ANC)
Necrotising pancreatitis
First 4 weeks
Fluid and dead tissue, not yet walled-off
Pancreatic pseudocyst
After interstitial disease
After 4 weeks
Encapsulated fluid, little or no necrosis
Walled-off necrosis (WON)
After necrotising disease
After 4 weeks
Encapsulated collection that still contains necrosis
Any of these can be sterile or infected. Older words such as “pancreatic abscess” and “phlegmon” were dropped in 2012. NHS lists cysts and pancreatic necrosis among complications; most people still recover fully. (Banks et al., Gut, 2013; NHS)
The determinant-based critical category is infected necrosis and persistent organ failure together — the sickest group in that system, not an Atlanta “stage 4”. (Dellinger et al., 2012)
This is not a cancer staging system. Pancreatitis is inflammation. Mayo Clinic Staff (page dated 31 October 2025) list pancreatic cancer among possible causes of pancreatitis and note higher cancer risk in long-standing chronic inflammation — that is a different disease. Hospital care is supportive: fluids, pain relief, nutrition, and treatment of the cause. There is no specific medicine that switches pancreatitis off. (Mayo Clinic; Mayo Clinic — Diagnosis & treatment; NIDDK)
Does Atlanta classify acute pancreatitis in four stages?
No. It uses three severity grades, two morphologic types, and early versus late phases. (Banks et al., Gut, 2013)
Why do people say “4 stages”?
They may mean the four collection types, or the four-category determinant-based system (mild, moderate, severe, critical). Neither is a numbered Atlanta stage list. (Banks et al.; Dellinger et al.)
What are the Atlanta diagnostic criteria of pancreatitis?
Two of three: typical pain; lipase or amylase at least three times the upper limit of normal; characteristic imaging. (Banks et al., Gut, 2013)
When does mild disease become severe?
Severe means persistent organ failure lasting more than 48 hours. Mild disease has neither organ failure nor local or systemic complications. (Banks et al., Gut, 2013)
Is necrotising pancreatitis a late stage?
No. It is a type of acute pancreatitis on imaging, not a numbered stage. See Necrotizing pancreatitis.
Can I stage myself at home from this table?
No. Classification is done in hospital. Sudden severe tummy pain is a reason to call 112, not to match yourself to a chart. (NHS)
This week’s pancreatitis roundup collects the dated, sourced items listed on our News page. Nothing here is new reporting: each item links to its original source so you can read it in full.
The International Association of Pancreatology (IAP) revised acute pancreatitis guidelines in 2025, endorsed by the European Pancreatic Club.
The first Ibero–Latin American acute pancreatitis guidelines (iLATAM-AP) were published in UEG Journal in 2026.
GBD 2021 data describe the global pancreatitis burden, including the East European peak.
The NHS reviewed its patient pages on acute pancreatitis (March 2026) and chronic pancreatitis (October 2025).
This page is for information only. It is not medical advice and does not replace a doctor. If you have severe abdominal pain, call 112 or go to hospital emergency care.
Manage Consent
To provide the best experiences, we use technologies like cookies to store and/or access device information. Consenting to these technologies will allow us to process data such as browsing behavior or unique IDs on this site. Not consenting or withdrawing consent, may adversely affect certain features and functions.
Functional
Always active
The technical storage or access is strictly necessary for the legitimate purpose of enabling the use of a specific service explicitly requested by the subscriber or user, or for the sole purpose of carrying out the transmission of a communication over an electronic communications network.
Preferences
The technical storage or access is necessary for the legitimate purpose of storing preferences that are not requested by the subscriber or user.
Statistics
The technical storage or access that is used exclusively for statistical purposes.The technical storage or access that is used exclusively for anonymous statistical purposes. Without a subpoena, voluntary compliance on the part of your Internet Service Provider, or additional records from a third party, information stored or retrieved for this purpose alone cannot usually be used to identify you.
Marketing
The technical storage or access is required to create user profiles to send advertising, or to track the user on a website or across several websites for similar marketing purposes.